


Every Open Shift
Why we’re building one system to connect clinicians, match them to demand, and handle the work of filling a shift.
On this page
For nearly a decade, healthcare staffing has debated how much software can do and how much depends on a relationship.
Think of an ICU shift opening at 4:30 a.m. A good recruiter knows whom to call. A useful system should already know who’s qualified, credentialed, available, and likely to accept.
I don’t think the relationship disappears. Software can do the preparation that makes a conversation useful, or help a clinician accept a shift without waiting for a call. We’ve seen similar changes in taxis, freight, lodging, and financial services.
AI expands the work software can handle, once the underlying workflow and its rules are in place.
A workforce in crisis: the biggest line on every hospital’s budget
Hospitals need more clinicians at the same time that experienced people are leaving the workforce.
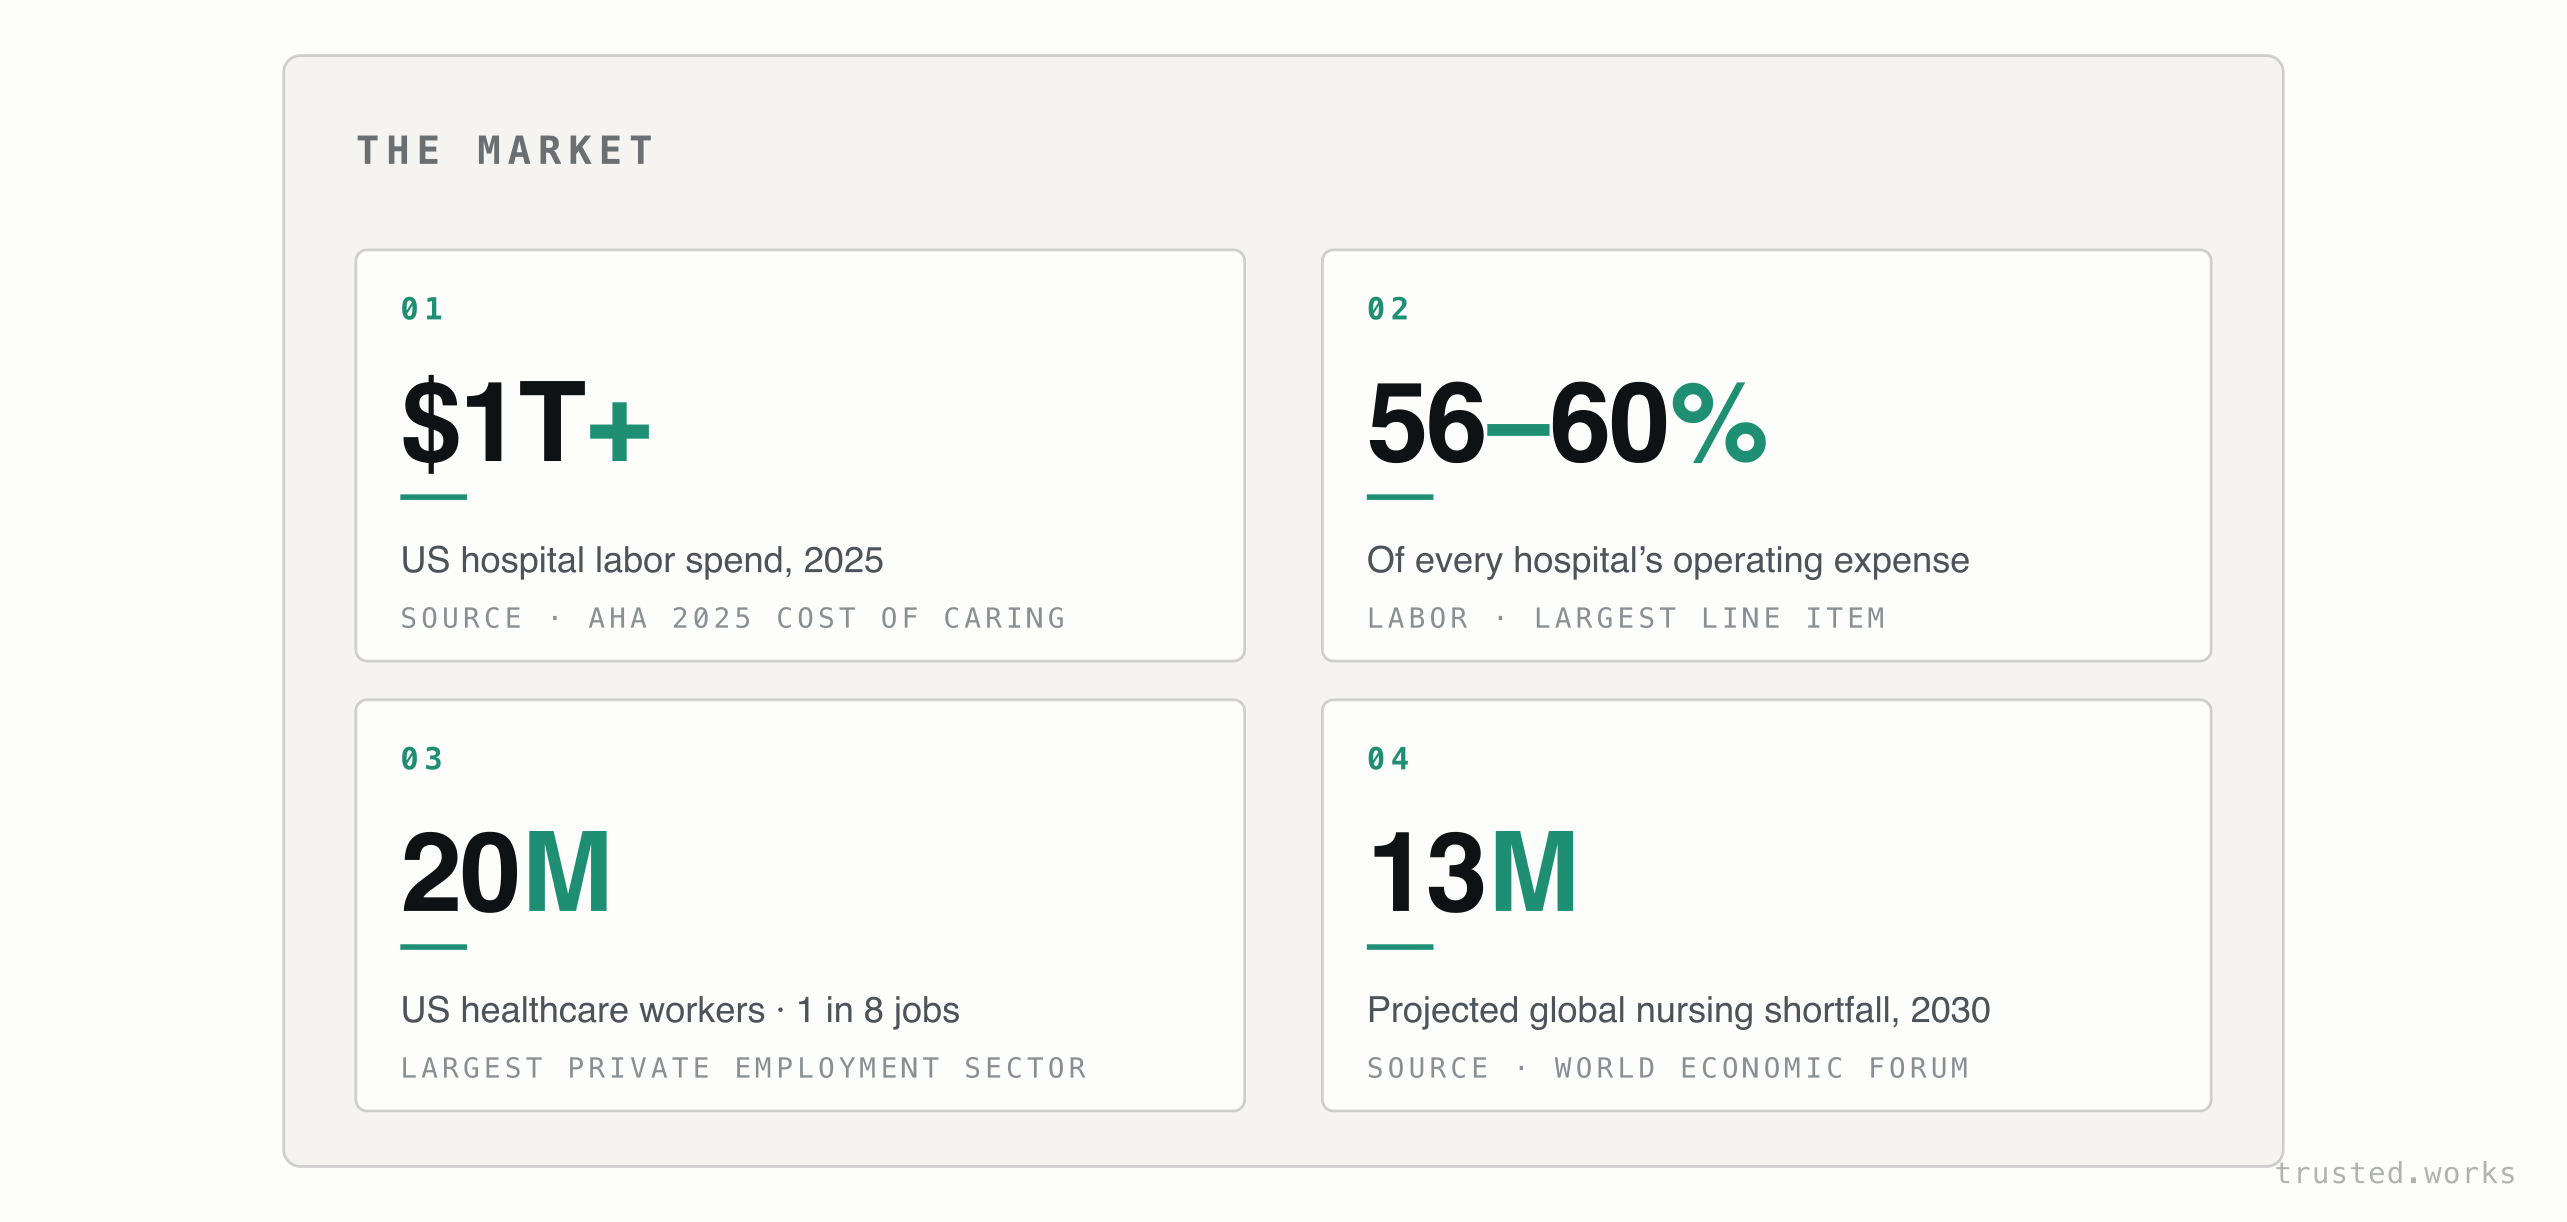
Demand is rising sharply under an aging population and a broadening definition of what counts as healthcare. Supply is contracting under retirements, burnout, and a thin new-entrant pipeline. The global nursing shortfall alone is projected at more than 13 million by 2030.
The numbers are worth pausing on. Healthcare is now the largest private employment sector in the United States. Roughly 20 million people work in it; about 1 in 8 American jobs. Hospital labor spend crossed $1 trillion in 2025. Labor is 56 to 60% of every hospital’s operating expense, the largest line item on the income statement of an industry approaching one-fifth of US GDP. No other operational decision a hospital makes carries comparable weight. Nothing comes close.
For most healthcare employers, the majority of clinical staff are permanent employees on fixed schedules. Sick leave, FMLA, census surges. Every day produces open shifts the schedule didn’t anticipate. Hospitals try to plug the gap with contingent labor: per diem locals picking up extra shifts, travel clinicians on three-month contracts. Both are expensive, slow to source, and most effective with lead time hospitals rarely have.
What remains falls to a nurse manager with a phone and a handful of levers: shift bonuses, text message requests sent in hope, last-minute calls and emails. The result is predictable. Labor cost climbs. Stress climbs with it. Morale and retention erode, accelerating the same supply problem the system was trying to manage. The biggest budget line in healthcare is being managed with the lowest-tech infrastructure in the building, by people whose actual job is to take care of patients.
No HR, nursing, or finance leader, given a clean sheet of paper, would design the system hospitals run today.
Today’s solutions all predate the World Wide Web. None was designed for an industry that flexes labor across W‑2, contract, per diem, and gig employment in real time. None was designed for AI. And yet this is the stack that fills the shifts in every operating room, ICU, ED, and inpatient unit in the country.
Internal labor is managed by one set of tools. External labor is managed by another. Each external pathway (per diem, travel, locums, allied) routes through different agencies, often with a Managed Service Provider (MSP) sitting on top to manage them. Hybrid programs get built from scratch. Most of the actual coordination happens in spreadsheets, in email, and on the phone.

What hospitals actually care about
For healthcare employers, three measures matter:
Fill rate: the percentage of open shifts that are adequately staffed.
Labor cost: direct compensation plus the indirect cost of incentives, agency markups, overtime, and intermediation.
Quality of care: the outcome everything else exists to produce.
These measures depend on each other. Filling a shift at an unsustainable cost creates a different problem; lowering cost without adequate staffing does too. We want the system to improve coverage, cost, and care together.
The operating system for the healthcare workforce
We’ve spent nearly a decade building a system to coordinate that work.
It connects work that has been spread across staffing agencies, VMS (Vendor Management System) tools, and scheduling software. As it handles more of the coordination itself, some of those separate tools become unnecessary.
We call it an operating system for the healthcare workforce. It keeps track of the resources involved, manages transactions, and gives other applications a consistent way to work with that information.
For clinical staffing, that means keeping shifts, clinicians, credentials, matches, and contracts in one system. Hospitals, clinicians, agencies, and internal float pools can coordinate through it. Nurse managers, partner agencies, and AI agents can work from the same records.
An OS at this scale, in this industry, can’t be pure software. Sequoia’s Julien Bek recently argued that the next generation of trillion-dollar companies won’t sell software at all. They’ll sell the work.
For every dollar spent on software, six are spent on services. --- Bek Abdullayev
Bek calls this the autopilot: software takes responsibility for delivering the work, beyond the assistance a copilot provides.
Healthcare workforce services, including staffing agencies, MSPs, credentialing teams, and scheduling consultancies, represent tens of billions of dollars. Much of that work exists because software hasn’t been able to coordinate staffing on its own. The result we’re working toward is a filled shift, with the work required to get someone there handled by the system.
Network. Intelligence. Rails.
That takes three things: access to clinicians, a way to match them to demand, and the workflows that get a matched clinician credentialed, scheduled, and paid.
| Network | Intelligence | Rails | |
|---|---|---|---|
| Job to be done | Access to enough supply | Match supply to demand, continuously | Turn a match into a filled, paid, credentialed shift |
| What it covers | Internal staff plus every external pathway on one substrate | Forecasting, dynamic pricing, clinical and preference matching | Credentialing, contracts, scheduling, invoicing, payments |
| What collapses without it | Decisions with no labor to execute against | A directory with no autopilot | A recommendation engine with no way to execute |

Network: access to enough supply. A hospital’s complete labor pool, internal staff and every external pathway (per diem, travel, agency, gig), unified on one substrate. Without a network that spans both sides, the system has decisions but no labor to execute against. The external side has to be deep enough to cover every employment model in real time. The internal side has to live in the same system as the external, so a shift can route to either pool without translation. And the network has to keep growing: at scale, recruiting, qualifying, retaining, and re-engaging clinicians is itself an autopilot problem. The same intelligence that fills shifts grows and rebalances the network underneath.
Intelligence: matching supply to demand, continuously. The agentic layer that forecasts labor need, prices open shifts in real time, and matches clinicians on both clinical fit and individual preferences. This is where the autopilot is most visible. Forecasting demand for a unit months out. Pricing shift incentives dynamically against the local labor market. Routing the right clinician to the right shift at the right time, while avoiding the schedules that push clinicians toward burnout. Proactively hiring contract workers to fill foreseeable gaps. The objective isn’t just filling shifts. It’s filling them in ways that respect clinician preferences and reduce burnout, the things that actually keep clinicians in the workforce.
Rails: the logistical workflows that turn matches into filled shifts. Validating and monitoring credentials. Executing contracts within policy. Approvals, scheduling, applicant tracking, invoicing, payments, supplier management. Automated where possible, AI-assisted where judgment is required. Without rails, you have a recommendation engine with no way to execute. The hard architectural ask is coordinating internal and external labor on one plane, in one data model, with one view of cost and utilization across every fulfillment channel.
A staffing company has the network and almost nothing else. A VMS has rails for one labor type. A scheduling system has rails for internal labor. HR platforms have some rails but no clinical depth and no clinician network. None of them has all three components. The compounding value comes from the data the three produce together: the substrate AI needs to actually deliver the outcome.
What this lets hospitals and clinicians do
With the OS and AI together, the math on hospital labor changes. Hospitals can finally operate their largest cost center with the precision they apply to every other major operational decision. Fill rates rise. Labor costs come down. Quality of care, which is what all of this is finally for, becomes more consistent. The labor pipeline that produces it is more reliable.

Today, people spend hours coordinating vendors and moving information between spreadsheets. A system that handles that coordination can reduce the number of handoffs, making staffing faster for hospitals and less expensive to run.
More importantly, it makes the experience meaningfully better for clinicians: higher pay, because the margin previously captured by intermediation flows through; faster matching, because the system is doing the work continuously instead of waiting on a phone tree; and a far simpler way to find and accept the work they want.
Where this goes
I expect every clinical workforce to use an operating system like this within ten years. Software made it possible to coordinate the work; AI is expanding how much of it the system can complete.
Healthcare staffing as it has been measured for thirty years will look different in five. The framing of agencies versus internal staff will collapse, because the OS doesn’t care which side of that line a clinician sits on. The economics that made the existing healthcare staffing leaders so prominent (margin spread on travel contracts) will compress, because the layer above them commoditizes the work. As a result, companies rebuilt around this layer will look very different from the ones that defined the previous era.
Trusted’s mission is to help people everywhere get care. That depends on getting clinicians to the patients who need them, shift by shift.
Check out our OS for the healthcare workforce at works.ai, and our flexible jobs marketplace for clinicians at trustedhealth.com.